Overview of Natural History of Meningioma

The natural history of meningioma refers to how these tumors develop, grow, and change over time. Although most meningiomas are slow-growing and noncancerous, their behavior can vary depending on their WHO grade, location, and individual characteristics. Understanding their natural history helps guide decisions about monitoring, diagnosis, and treatment when necessary.
What Is a Meningioma?
Meningiomas are typically slow-growing, benign tumors originating from the protective membranes surrounding the brain and spinal cord. Their natural history varies; many remain stable or grow slowly, while others expand rapidly, causing symptoms related to localized compression of brain tissue and cranial nerves.
Meningiomas are the most frequent primary tumor of the brain and spinal cord, originating from the membranes around the brain (meninges) and compressing the brain (Figure 1). According to their appearance and behavior, these tumors are classified into one of three grades. Most meningiomas are benign (i.e., Grade I). These tumors can be incidental findings due to the widespread use of radiographic imaging tests to evaluate other conditions.
Their definitive diagnosis is established with patient history, physical examination, imaging tests, and tumor sampling. Meningiomas’ characteristic imaging pattern is their hallmark identifier. In general, meningiomas are asymptomatic and measure around 3 cm in diameter. However, if symptoms appear, they correspond with tumor size and location as well as their ability to cause local brain swelling. It is not entirely known what causes meningiomas.
Factors that increase their occurrence include age, family history, genetic disorders, and environmental exposures. The knowledge and understanding of the natural history of meningiomas is important to provide treatment and support to patients and their families.
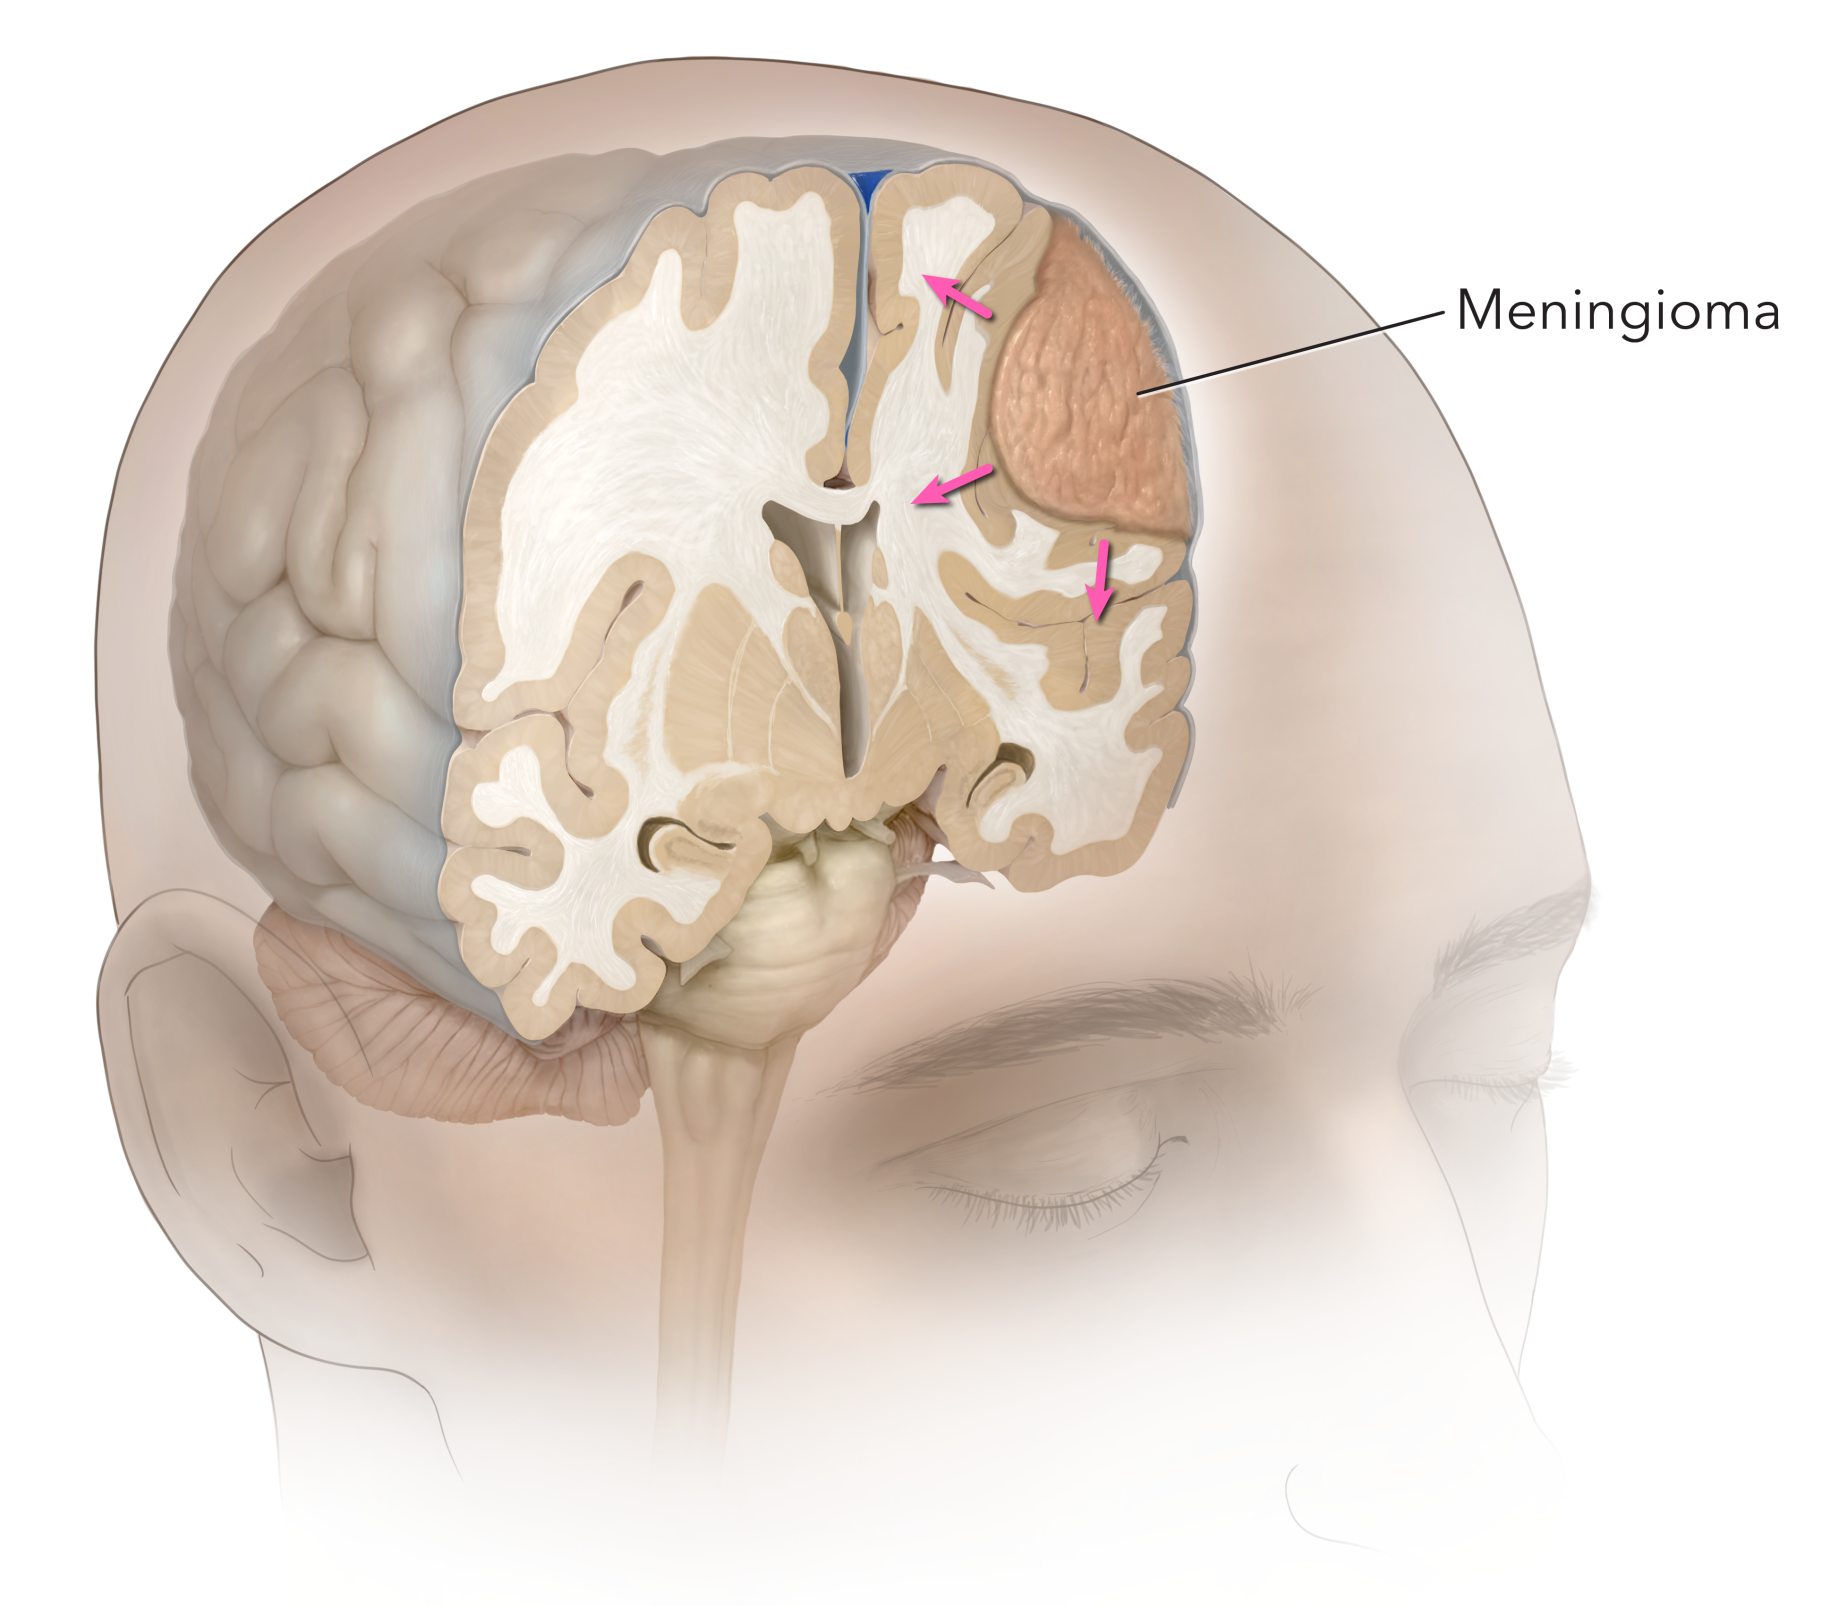
Figure 1. A left frontal meningioma originating from the covering of the brain (meninges) and compressing the brain is demonstrated.
Cancer and Meningiomas
Determining whether a meningioma is cancerous or non-cancerous is critical. A cancerous meningioma has the potential to invade the surrounding brain and related structures, making it difficult to completely remove. In contrast, non-cancerous meningiomas will push against, instead of invade, the brain and can be more easily removed. If a non-cancerous tumor causes problematic symptoms, it is typically cured by complete surgical removal.
To better understand the nature of the tumor, meningiomas are classified according to their cellular features into one of three grades of the established World Health Organization (WHO) classification. Characteristics such as growth rate and the appearance of cells under the microscope guide the grading and provide insight into the possibility of recurrence following surgery. Grade I tumors are most common. In fact, more than 80% of meningiomas are believed to be Grade I tumors. These types of tumors are benign, slow-growing, and carry the lowest likelihood of recurrence following surgery.
Grade II tumors have a faster growth rate and can invade the surrounding structures. Their treatment can be more challenging, with a higher chance of recurrence. Finally, Grade III tumors are aggressive cancerous lesions that grow and spread quickly. Their management is complex and specific.
Meningiomas can have variable sizes depending on their grade and time of diagnosis. Studies have shown that most of them measure around 3 cm when discovered. Their growth rate is around 2-4 mm per year. Importantly, size is not always the determining factor for surgery. Instead, a combination of factors related to the tumor and the patient are considered to determine the treatment course. For instance, if the tumor growth and location affect vital brain structures and/or cranial nerves, the situation may require prompt surgical management.
Several types of meningiomas are curable. They can be treated with surgery, radiation, observation, or a combination of treatments. Small asymptomatic lesions can be observed and maintained under surveillance imaging without invasive management (Figure 2). If surgery is performed, the goal is to extract the tumor completely, preserving adjacent critical structures. Every patient is unique, and treatment is tailored accordingly. The involvement of a multidisciplinary team including neurosurgeons, oncologists, and radiation specialists favors the best possible outcomes.
Why should you have your surgery with Dr. Cohen?
Dr. Cohen
- 7,500+ specialized surgeries performed by your chosen surgeon
- More personalized care
- Extensive experience = higher success rate and quicker recovery times
Major Health Centers
- No control over choosing the surgeon caring for you
- One-size-fits-all care
- Less specialization
For more reasons, please click here.

Figure 2. Red arrow pointing to a small incidental meningioma
Diagnosing Meningiomas
Although meningiomas are slow-growing tumors, their symptoms are related to their location and compression of surrounding brain structures.
Common general symptoms are headaches, nausea, and vomiting. Even small-sized tumors can cause significant symptoms if they affect brain areas that are more sensitive to compression (i.e., optic nerves) or cause brain swelling due to their more invasive nature.
Considering the general principle that different parts of the brain and spinal cord control unique body functions, meningiomas can cause symptoms secondary to the location in which they arise. For example, if a tumor compresses the optic nerves, the patient will experience visual alterations. Of note, symptoms are suggestive but not definitive of an anatomic location.
Here are some of the most common locations of meningiomas and the symptoms they produce.
Intraventricular Meningiomas
Intraventricular meningiomas occur in the brain’s internal cavities (i.e., ventricles) where cerebrospinal fluid flows. The pressure within this system and the cranium increases when the tumor obstructs the flow of this fluid. Symptoms include headaches, nausea and vomiting, lethargy, and vision changes.
Parasagittal Meningiomas
Parasagittal meningiomas occur in the middle or slightly to one side of the brain near its surface. They can cause seizures, personality changes, and leg weakness.
Falcine Meningiomas
Falcine meningiomas occur in the membrane that separates the right and left sides of the brain. This region controls several cognitive and personality functions. Symptoms can include muscle weakness and visual alterations.
Clival Meningiomas
Clival meningiomas occur in the back of the skull. They can produce symptoms that include alterations in coordination, swallowing, walking, and hearing.
Convexity Meningiomas
Convexity meningiomas arise on the brain’s surface. If the motor region is affected, they can produce weakness or paralysis on the opposite side of the lesion.
Foramen Magnum Meningiomas
Foramen magnum meningioma affects the largest hole of the skull where the spinal cord enters the cranium at the skull base. Because space is limited, compression can quickly affect balance, strength, sensation, and cranial nerve function.
Olfactory Groove Meningiomas
Olfactory groove meningiomas affect the base of the frontal lobes and nerves responsible for smell, so they cause personality changes or a loss of smell.
Cerebellar Meningiomas
Cerebellar meningiomas affect the cerebellum and cause changes in balance and coordination.
Suprasellar Meningiomas
Suprasellar meningiomas commonly affect the pituitary gland and may produce visual decline due to the vicinity of the optic nerves.
Interestingly, meningiomas can be grouped, distinguished, and treated according to the anatomic location from which they arise. Neurosurgeons are trained to evaluate the presenting symptoms and determine a treatment plan.
Symptoms of Meningiomas by Location
Although meningiomas are slow-growing tumors, their symptoms can be related to their location and compression of surrounding brain structures. Common general symptoms are headaches, nausea and vomiting. Even small-sized tumors can cause significant symptoms if they affect brain areas that are more sensitive to compression (i.e., optic nerves) or cause brain swelling due to their more invasive nature.
Considering the general principle that different parts of the brain and spinal cord control unique body functions, meningiomas can cause symptoms secondary to the location in which they arise. For example, if a tumor compresses the optic nerves, the patient will experience visual alterations. Of note, symptoms are suggestive but not definitive to an anatomic location.
Here are some of the most common locations of meningiomas and the symptoms they produce. Intraventricular meningiomas occur in the internal cavities of the brain (i.e., ventricles) where cerebrospinal fluid flows. The pressure within this system and the cranium elevates when the tumor obstructs the flow of this fluid. Symptoms include headaches, nausea and vomiting, lethargy, and vision changes.
Parasagittal meningiomas occur in the middle or slightly to one side of the brain near its surface. They can cause seizures, personality changes, and leg weakness. Falcine meningiomas occur in the membrane that separates the right and left sides of the brain. This region controls several cognitive and personality functions. Symptoms can be muscle weakness and visual alterations. Clival meningiomas occur in the back of the skull. They can produce symptoms including alterations in coordination, swallowing, walking, and hearing.
Convexity meningiomas arise on the surface of the brain. If the motor region is affected, they can produce weakness or paralysis on the opposite side of the lesion. Foramen magnum meningioma affects the largest hole of the skull where the spinal cord enters the cranium at the base of the skull. The space is limited, so compression occurs quickly and causes alterations in balance, strength, sensorium, and cranial nerves.
Olfactory groove meningiomas affect the base of the frontal lobes and nerves responsible for smell, so they cause personality changes or a loss of smell. Cerebellar meningiomas affect the cerebellum and cause changes in balance and coordination. Suprasellar meningiomas commonly affect the pituitary gland and may produce visual decline due to the vicinity of optic nerves.
Interestingly, meningiomas can be grouped, distinguished, and treated according to the anatomic location from which they arise. Neurosurgeons are trained to evaluate the presenting symptoms and determine a treatment plan.
Causes of Meningiomas
The causes of meningiomas are variable and are related to factors such as age, race, gender, environmental factors (i.e., radiation exposure), and genetic diseases.
Age: Meningiomas are uncommon in children and adults less than 20 years of age. However, the risk of their development increases with age, and most meningiomas are found in patients older than 65 years.
Race: Non-Hispanic African American patients are at an increased risk of meningioma development compared to other races.
Gender: Being female slightly increases the risk of these tumors developing. Studies have found that meningioma incidence is higher in post-pubertal women than in men.
Hormones: Some meningiomas change size during the menstrual cycle and pregnancy. Furthermore, some meningiomas have cell receptors that are affected by hormones.
Family History: People with a family history of meningiomas have an increased risk of these tumors.
Genetic Disorders: Specific genetic disorders are associated with meningioma development.
Ionizing Radiation: Ionizing radiation is the principal environmental risk factor associated with meningioma development. This association was found valid in several scientific studies where people with a history of high-dose exposure to ionizing radiation had an increased incidence of meningiomas.
Should I get a second opinion if my doctor recommends monitoring?
Yes. Many patients seek a second opinion to help them better understand whether observation is still the safest option. An expert review of your MRI can help estimate the tumor's growth pattern, assess its proximity to critical brain structures, and determine whether your current management plan remains appropriate.
Expert Meningioma Evaluation and Second Opinions
Choosing the right approach for a meningioma depends on its size, location, growth pattern, symptoms, and relationship to critical brain structures. While some meningiomas can be safely monitored, others may require surgical or radiation treatment.
Dr. Aaron Cohen-Gadol provides expert neurosurgical evaluations for patients seeking a clearer understanding of their diagnosis and treatment options. Reviewing your imaging and medical history can help determine which approach may be appropriate for your individual case.
Summary
In most cases, meningiomas are benign and asymptomatic. They arise from the meningeal layers that cover and protect the brain and spinal cord. An imaging study such as a head CT or an MRI is used to diagnose meningiomas. Signs and symptoms depend on the tumor size and location. Some of them do not produce symptoms. Therefore, they are discovered incidentally in the investigation of a different condition.
Common symptoms include headache, dizziness, nausea and vomiting, and visual impairments. The specific causes of meningiomas have not been identified. However, there are certain known risk factors. Therefore, a multidisciplinary team management approach is suggested to enhance patient outcomes.
FAQs
Can a meningioma stop growing on its own?
Yes. Many meningiomas, particularly small WHO Grade I tumors, grow very slowly or remain stable for years without causing symptoms. However, growth patterns vary, and some tumors may enlarge over time. Regular MRI surveillance is essential to detect changes early and determine whether continued observation remains appropriate.
Does a growing meningioma always require surgery?
Not necessarily. A growing meningioma does not automatically mean surgery is needed. The treatment decision depends on the rate of growth, tumor location, symptoms, age, overall health, and the potential risks and benefits of intervention. Some patients may continue with observation or be candidates for radiation therapy instead of surgery.
Can I naturally stop a meningioma from growing?
There is currently no proven natural remedy, diet, or supplement that can stop a meningioma from growing. Regular MRI monitoring can help track changes, while treatment options such as surgery or radiation therapy may be considered if the tumor grows or causes symptoms. The appropriate medical approach depends on the tumor’s characteristics and should be discussed with a neurosurgeon.
Can stress cause a meningioma to grow?
There is currently no strong scientific evidence that stress directly causes a meningioma to grow. Although stress management may support overall well-being, it has not been proven to prevent tumor growth. Regular medical follow-up and MRI scans remain important for monitoring the tumor.
Key Takeaways
- Meningiomas are the most common primary central nervous system tumor. The majority of them are benign Grade I tumors that grow slowly. However, Grade II and III tumors have more aggressive and cancerous behavior.
- Diagnosing meningiomas requires a combination of patient history, physical examination, and imaging tests.
- Signs and symptoms of meningiomas depend on their size and location. Some of them may not produce symptoms. Some symptoms are headaches, dizziness, nausea and vomiting, and neurologic deficits.
- Factors that increase the risk of meningioma are age, family history, genetic disorders, and environmental exposures.